Charcot foot is a weakening and collapse of the foot bones in people with diabetic nerve damage. Early signs, offloading, daily foot care and limb-salvage surgery explained.
On this page 8 sections
- What is Charcot foot and why does it develop?
- Symptoms of Charcot foot: recognising the early stage
- Stages and diagnosis of Charcot foot
- Treatment in the active stage: offloading the foot
- Limb-salvage surgery for Charcot foot: who needs it and how is it done?
- Daily foot care and prevention
- When should you see a doctor?
- Key points
Charcot foot (Charcot neuroarthropathy) is a condition in which the bones and joints of the foot and ankle weaken, fracture and shift out of position in people with nerve damage (neuropathy), most often caused by diabetes, so that the shape of the foot gradually changes. In the early stage it usually appears as a warm, red, swollen foot; because sensation is reduced, the pain may be less than expected, and it can easily be mistaken for an infection, a sprain or a blood clot. Early diagnosis and offloading the foot help to limit progression of the deformity. When marked deformity, a non-healing ulcer or infection develops, reconstructive surgery aimed at saving the foot, known as limb-salvage surgery, may be considered.
Managing Charcot foot is a team effort: diabetes control, circulation, wound care and orthopaedic treatment are planned together. This article explains the symptoms, stages, treatment options and daily foot care in plain language.
What is Charcot foot and why does it develop?
Long-standing diabetes can damage the nerves in the feet. When protective sensation is reduced, a person may not notice minor injuries, sprains or small cracks in the bone and keeps walking on the foot. At the same time, nerve damage affects blood flow to the bones and bone structure, making the bones weaker. When an unnoticed injury, continued loading and the body's inflammatory response come together, bones fracture and joints slip out of alignment.
Charcot foot most often affects the midfoot. Here, collapse of the arch can make the sole curve downwards, a shape known as a "rocker-bottom" deformity. The ankle and hindfoot can also be involved. Apart from diabetes, nerve damage related to alcohol and some spinal cord conditions can produce a similar picture.
Symptoms of Charcot foot: recognising the early stage
Recognising the early stage is a key step in shaping how treatment goes. In a person with neuropathy, the following signs need attention:
- One foot feeling noticeably warmer than the other
- Swelling and redness of the foot or ankle
- Mild to moderate pain or discomfort; some people have no pain at all
- A feeling of instability, or a shoe that suddenly feels too tight
- Later, collapse of the arch and a change in the shape of the foot
- Calluses or ulcers over bony prominences
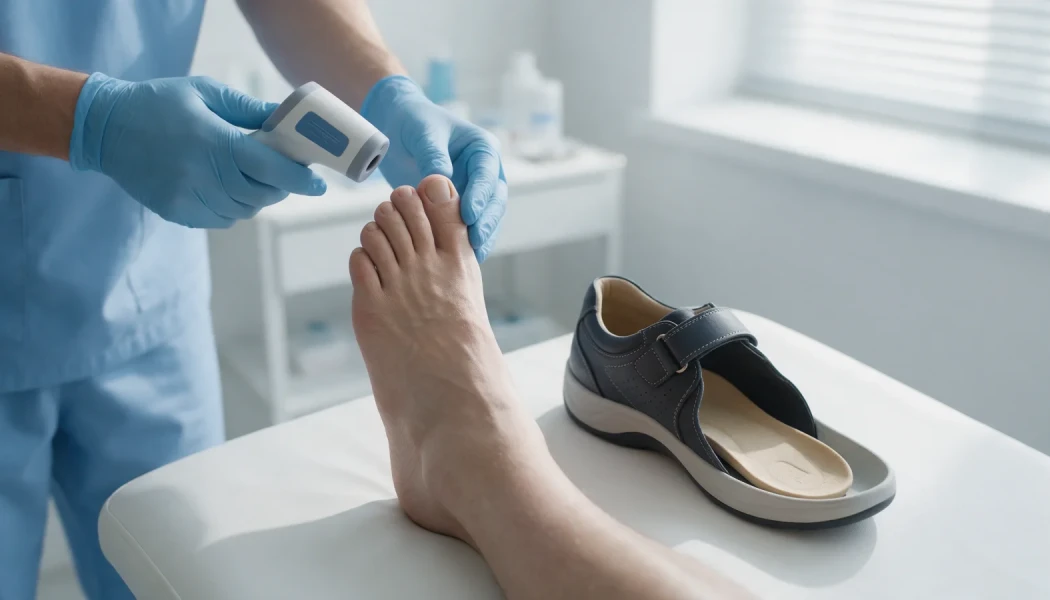
This picture is often confused with soft-tissue infection, gout, a sprain or a deep vein thrombosis. The doctor distinguishes between them by measuring the temperature difference between the two feet and arranging imaging. In a person with diabetes, an unexplained warm, swollen foot should be assessed for Charcot foot until proven otherwise.
Stages and diagnosis of Charcot foot
Charcot foot passes through different stages over time. Knowing the stage determines when and how treatment is given.
| Stage | What happens | General approach |
|---|---|---|
| Early stage | Warm, swollen foot; X-ray may be normal, MRI shows bone marrow oedema | Prompt diagnosis and immediate offloading |
| Active (fragmentation) stage | Bones fracture and joints shift; swelling and warmth are marked | Offloading in a total contact cast or suitable orthosis |
| Coalescence stage | Warmth and swelling settle; bone fragments begin to heal | Protected, gradual weight-bearing |
| Reconstruction stage | The foot is cool and stable; an established change in shape may remain | Custom footwear and insoles; surgery if needed |
Diagnosis begins with the history and examination. Testing sensation, checking the pulses and measuring the temperature difference between the feet provide important clues. Weight-bearing X-rays of both feet are used to assess the deformity and monitor progression, but they may be normal in the early stage, so an MRI is requested if Charcot foot is suspected. Where there is an ulcer and infection is suspected, blood tests, further imaging and sometimes a bone biopsy are used to look for bone infection (osteomyelitis). You can read about how infection is managed on our page on bone and soft tissue infections and in our article on bone infection treatment. If surgery is planned, the circulation in the leg also needs to be assessed together with vascular specialists.
Treatment in the active stage: offloading the foot
In the active stage, treatment centres on taking weight off the foot so that the bones can heal without further collapse. The main methods are:
- Total contact cast: a cast moulded closely to the shape of the foot and leg that spreads pressure over a large area. It is usually changed at regular intervals as the swelling goes down.
- Knee-high walking boots and custom orthoses: these may be used in suitable patients or after the cast stage.
- Mobility aids: crutches, a walking frame or a wheelchair reduce the load on the foot.
- Regular reviews: temperature differences and X-rays are used to check whether the active stage has settled.
The active stage often lasts several months, and its length varies from person to person. Once the foot has settled, custom footwear and insoles are introduced. Blood glucose control, nutrition, stopping smoking and protecting the other foot are also part of treatment, because while one foot is offloaded, the other carries more weight.
Limb-salvage surgery for Charcot foot: who needs it and how is it done?
Some people with Charcot foot can be managed without surgery, with offloading and suitable footwear. Surgery is considered in situations such as:
- An unstable deformity that cannot be controlled with an orthosis or footwear
- Ulcers over a bony prominence that do not heal or keep coming back
- Bone infection that needs surgical cleaning
- Marked instability of the ankle
The surgical option depends on where the deformity is, how severe it is, and whether there is an ulcer or infection. If a single bony prominence on an otherwise stable foot is causing an ulcer, removing the prominence may be enough. For more marked deformities, the foot is realigned and certain joints are fused in a corrected position (arthrodesis). This correction may be held with internal fixation, such as plates, screws and rods inside the bone, or with a circular external fixator.
A circular external fixator (Ilizarov frame) can be particularly useful for patients with an open wound or infection, poor bone quality or fragile soft tissues. Because the rings and wires sit outside the body, the foot can be stabilised without placing large metal implants in an infected area, the deformity can be corrected gradually if needed, and treatment can be planned in stages. You can read more about the principles of this approach on our page on Ilizarov and limb reconstruction surgery and in our article what is Ilizarov surgery?
Recovery after limb-salvage surgery is usually a long process; months of protected weight-bearing may be needed, followed by lifelong use of custom footwear. Because there are risks such as wound problems, infection and failure of the bones to unite, the decision takes into account general health, blood glucose control, circulation and the patient's expectations together. For some patients, foot salvage and other options are discussed openly and weighed up jointly by the patient and the team.
Daily foot care and prevention
For people at risk of, or treated for, Charcot foot, daily habits matter a great deal:
- Check your feet every day, using a mirror if needed, for redness, swelling, ulcers and calluses.
- Do not walk barefoot, even at home.
- Wear well-fitting shoes that do not rub, and the insoles you have been prescribed.
- Aim to keep your blood glucose within the targets your doctor recommends, and seek support to stop smoking if you smoke.
- Keep up with your diabetic foot checks, including regular sensation and circulation assessments.
- If one foot becomes clearly warmer and more swollen than the other, limit walking on it and seek assessment without delay.
When should you see a doctor?
People with diabetes or reduced sensation in their feet should be assessed on the same day, or as soon as possible, if they notice:
- An unexplained warm, red and swollen foot or ankle
- A newly noticed change in the shape of the foot, or collapse of the arch
- An ulcer, discharge or unpleasant smell on the sole or side of the foot
- Foot symptoms together with fever, shivering or unexplained worsening of blood glucose
- A new sore, rubbing or increasing swelling while wearing a cast or orthosis
Prof. Dr. Halil İbrahim Balcı is a co-editor of an international textbook on external fixator applications according to Ilizarov principles. In Charcot foot, treatment is planned individually on the basis of examination and imaging findings, together with specialists in diabetes, vascular surgery and infectious diseases.
Key points
- Charcot foot is a weakening and collapse of the foot bones and joints in people with diabetic nerve damage.
- The early sign is often a warm, red, swollen foot, and pain may be less than expected.
- X-rays may be normal early on; if Charcot foot is suspected, an MRI is used.
- In the active stage, the mainstay of treatment is offloading in a total contact cast or suitable orthosis.
- For unstable deformity, non-healing ulcers or infection, limb-salvage surgery with internal fixation or an Ilizarov frame may be considered.
Frequently Asked Questions
With appropriate offloading, the active stage of Charcot foot settles over time and the bones heal. However, any change in shape that has developed does not correct itself. With mild deformity, daily life can often continue with custom footwear and insoles, whereas marked deformity may need surgery. Lifelong foot protection and regular check-ups are recommended after the active stage, and the course varies from person to person.
Both can cause a warm, red, swollen foot, so telling them apart is not always easy. An open wound, fever and raised inflammatory markers in blood tests point towards infection. The doctor considers the examination, blood tests and imaging such as MRI together, and a bone biopsy may be taken if needed. Both conditions can also be present in the same foot at the same time.
Offloading in a total contact cast or a similar orthosis continues until the active stage has settled. This often takes several months and may take longer in some people. The cast is changed at regular intervals as the swelling goes down. Whether the foot has settled is judged by a reduced temperature difference between the feet and by X-ray findings, after which custom footwear is introduced gradually.
Yes. Because nerve damage usually affects both feet, Charcot foot can develop in the other foot over time. While one foot is in a cast, the other carries more load, so the unaffected foot should also be checked regularly during this period. If you notice increased warmth, swelling or redness in the other foot, see your doctor without delay.
The timing depends on the type of operation, the fixation method used and how quickly the bones unite. After fusion surgery, protected or limited weight-bearing is usually needed for several months. With an external fixator, the process follows the stages set by the surgeon. Weight-bearing is increased gradually after X-rays have been reviewed at follow-up, and custom footwear is then introduced.
This article is for general information only and does not replace a medical examination, diagnosis or treatment. Treatment options and outcomes vary from person to person.
Related treatment area Bone Infection Treatment: Osteomyelitis and Soft Tissue Infections